
Definition
Proximal hamstring tendinopathy is a chronic painful condition of the common tendon of the hamstring muscles, where it inserts on the lower part of the ischium. It mainly presents as deep pain in the lower buttock, sometimes difficult to pinpoint, which appears or worsens during activities that place heavy demands on the hamstrings: fast running, accelerations, sprinting, uphill running, changes of direction, jumps or prolonged sitting.
It is particularly common in distance runners, sprinters, footballers, rugby players, dancers and athletes whose activities require rapid hip flexion movements combined with knee extension.
The term “tendinitis” is commonly used, but “proximal hamstring tendinopathy” is generally more appropriate: the condition corresponds more to a disruption of the tendon’s structure and mechanical capacity than to simple acute inflammation. It can appear gradually, without any clearly identified trauma, or follow an initial episode of overload or a musculotendinous injury that was not adequately rehabilitated.
Anatomy
The hamstrings mainly comprise the biceps femoris, the semitendinosus and the semimembranosus. The biceps femoris has two heads: a long head and a short head. Proximally, the semitendinosus and the long head of the biceps femoris share a common origin at the ischial tuberosity, while the semimembranosus has a separate but adjacent proximal insertion.
This anatomical arrangement explains why the pain is generally felt at the proximal origin of the hamstrings, just below the gluteal fold. The proximal tendon lies in an anatomical region simultaneously subjected to tensile stresses, compressive stresses, hip and knee movements, and the forces generated during running and sprinting.
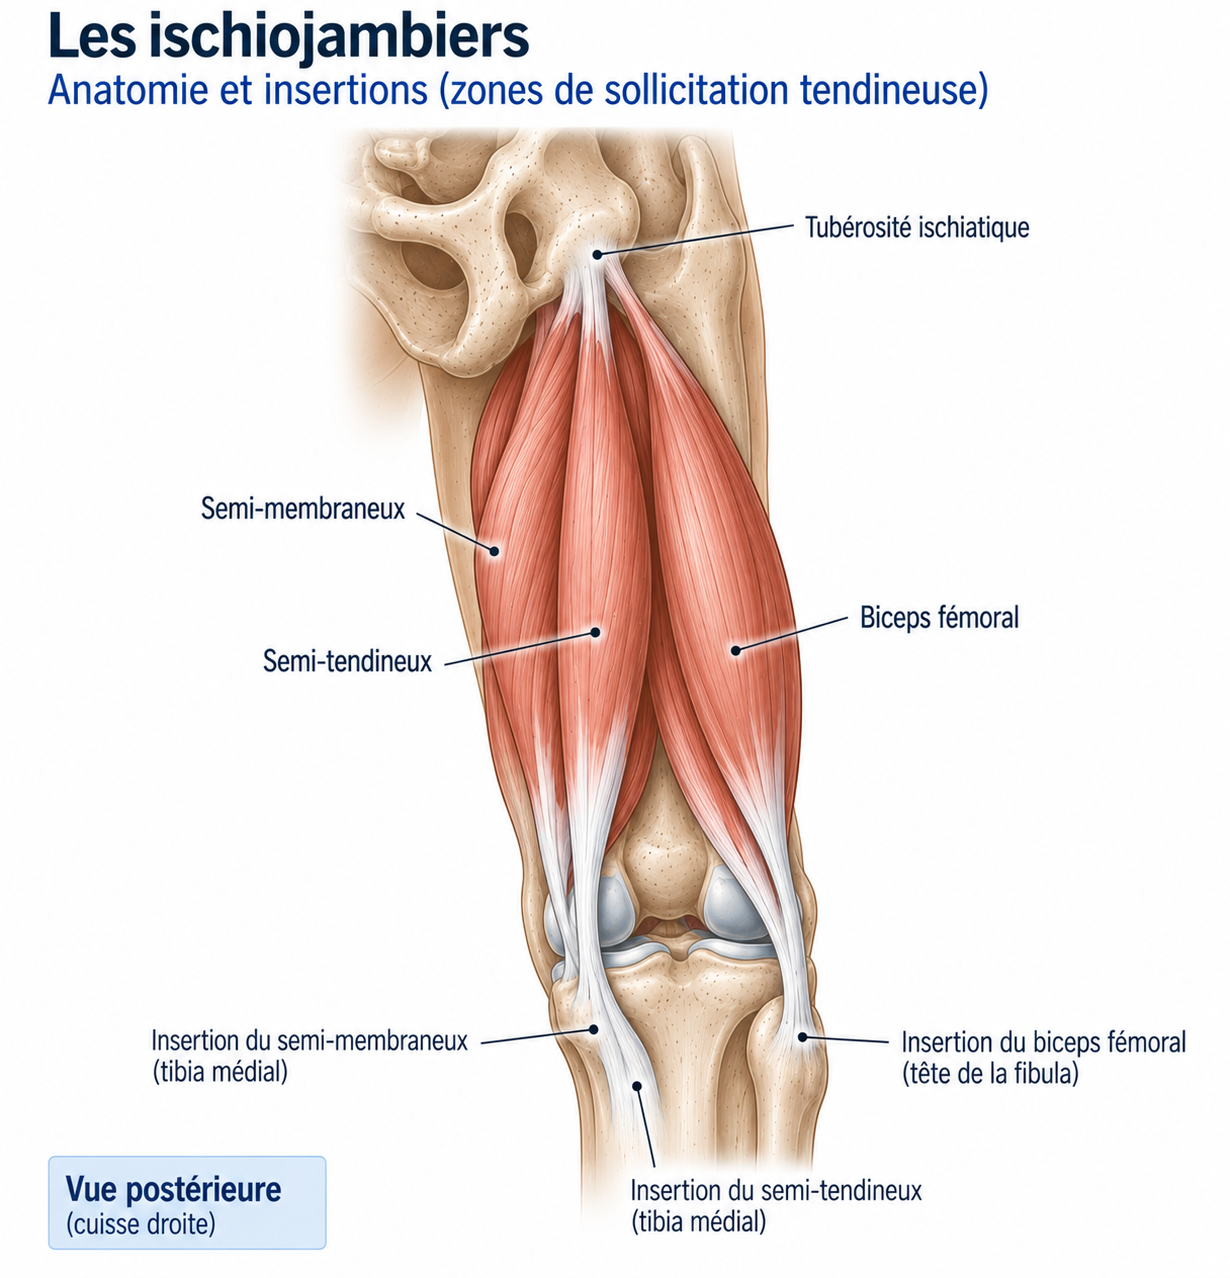
🔍 Click on the image to enlarge it
Function of the hamstrings
The hamstrings contribute to hip extension (running, accelerations, climbing stairs, pushing movements, jumps) and to knee flexion. They also play an important role in the dynamic stabilisation of the knee and pelvis, and help brake the lower limb during fast running by controlling the movement of the leg before ground contact. They must therefore be able to produce and absorb large forces at high speed.
Biomechanics: why the tendon becomes painful
Tendinopathy generally appears when there is an imbalance between the load applied to the tendon and its capacity to withstand it. Certain situations are particularly demanding for the proximal tendon: marked hip flexion combined with knee extension places the tendon under high tension, which is notably the case during fast running and accelerations. A strongly flexed hip position also increases compression of the tendon against the ischial tuberosity — an important concept in rehabilitation, because some positions are painful not only because they stretch the tendon, but also because they increase its compression.
A common mistake is to regard hamstring pain as the result of a lack of flexibility. Yet in proximal tendinopathy, systematically trying to “stretch the tendon” can sometimes perpetuate the symptoms: stretches combining hip flexion and knee extension place the proximal tendon precisely in a position of high tension and compression. Management therefore aims to gradually restore the tendon’s capacity to withstand these stresses rather than to avoid these positions permanently.
Epidemiology
Proximal hamstring tendinopathy frequently affects distance runners and sprinters, but also footballers, rugby players and dancers — more generally, all athletes whose activities require rapid hip flexion movements combined with knee extension (sprinting, accelerations, changes of direction).
It can also affect people who do little sport, notably through pain triggered by prolonged sitting. A change in training load (introducing sprints, fast intervals, hills or speed work) is often more decisive in the onset of symptoms than the presence of any particular anatomical abnormality.
Causes & risk factors
Proximal hamstring tendinopathy generally appears when there is an imbalance between the load applied to the tendon and its capacity to withstand it. Several factors can promote its onset.
Training load factors
A sudden increase in training volume or intensity, too rapid a return after a break, a large increase in mileage, the recent introduction of interval sessions, a return to sprinting, more hill sessions or strength exercises that place heavy demands on the hamstrings are the main load factors. A runner may tolerate a given weekly volume perfectly well and then develop pain after abruptly introducing sprint sessions, fast intervals, hills or speed work.
Biomechanical factors
High exposure to hip flexion, hamstring weakness, a strength deficit in the posterior chain, a lumbopelvic control deficit or poor tolerance of loads at long muscle lengths also promote the onset of symptoms.
Symptoms
The classic picture is that of an athlete describing deep pain in the buttock, just below the gluteal fold, appearing during fast running or after sessions. At first, the pain may be mild and present only after training, the next day or after a fast session; it may then gradually appear during activity. At a more advanced stage, it can become troublesome when sitting, driving, running slowly, going uphill or doing strengthening exercises. Its distinctive feature is often its insidious and chronic nature.
The main symptom is low buttock pain, generally located in the lower part of the buttock, near the ischial tuberosity, sometimes slightly more medial or lateral. It may be described as deep, dull, localised and sometimes burning. It typically appears when accelerating, sprinting, taking long strides, running uphill or changing pace, and may be worse a few hours after training or the next day — a phenomenon that is particularly important to monitor as the load is progressed.
Prolonged sitting can become particularly uncomfortable: the patient tends to change position regularly, sit on one buttock, use a cushion or avoid hard seats. This feature is highly suggestive when the pain is clearly located at the origin of the hamstrings.
Clinical examination
The examination should look at the precise location of the pain, reproduction of symptoms, hamstring strength, tolerance to lengthening, lumbopelvic function and any neurological signs. However, no single test can establish the diagnosis with certainty: it relies on the consistency between the clinical history, the location of the pain and several provocation tests.
Palpation looks for tenderness at the ischial tuberosity and the common hamstring origin — pain reproduced precisely at this spot is an important finding, although simple local tenderness is not enough to establish the diagnosis. Provocation tests generally put the hamstrings under tension by combining hip flexion and knee extension, sometimes with an added resisted contraction; reproduction of the usual pain is more informative than a simple stretching sensation.
Strength assessment looks for reduced strength in knee flexion or hip extension, a right/left asymmetry, or poor tolerance of slow and fast contractions — but maximal strength alone is not enough: an athlete may have normal strength on manual testing yet be unable to cope with repeated sprints, changes of pace or high-speed running; functional capacity must therefore be assessed progressively.
Posterior buttock pain is not always tendinopathy: the neurological examination looks for radiation below the buttock, pain running down the thigh, paraesthesia, numbness, motor weakness or changes in reflexes, which would point towards irritation of the sciatic nerve or a lumbar origin.
Further tests
Ultrasound
May show tendon thickening, changes in echotexture, insertional abnormalities, hypervascularisation, a partial tear or associated bursopathy. Allows comparison with the opposite side and dynamic assessment.
MRI
Particularly useful in chronic or complex forms: tendon thickening, signal abnormalities, peritendinous oedema, insertional involvement, partial tear or avulsion. Helps rule out certain differential diagnoses.
Differential diagnoses
Lumbar radiculopathy
To be considered in the presence of radiating pain, paraesthesia, a neurological deficit or associated low back pain.
Deep gluteal syndrome
Compression or irritation of the sciatic nerve in the gluteal region can reproduce similar pain.
Sacroiliac joint involvement
Can cause buttock pain that is sometimes difficult to distinguish from proximal tendinopathy.
Hip disorders
An intra-articular disorder can sometimes be felt in the buttock region.
Ischial bursopathy
Can cause significant pain when sitting, mimicking proximal tendinopathy.
Acute muscle tear
Acute pain that comes on during a sprint should prompt a search for a musculotendinous injury rather than simple tendinopathy.
Proximal hamstring avulsion
A much more serious form, occurring with a sudden mechanism (marked hip flexion + knee extension), with a snapping sensation, bruising and significant loss of strength.
Classification
Stage 1
Pain linked to certain loads: it appears mainly after training, during intense efforts or sprinting. Slow running generally remains possible.
Stage 2
Pain during activity: it appears during running, accelerations or strengthening exercises. Performance starts to decline.
Stage 3
Pain during daily activities: it becomes present when sitting, during certain movements, and sometimes when walking.
Stage 4
Severe involvement or associated injury: a significant tear, an avulsion or a major loss of strength should prompt consideration of specialist management.
Treatment
Phase 1 — Reducing irritability
Complete rest is generally not the answer: on the contrary, it leads to a reduction in tendon capacity. The aim of this first phase is to reduce pain, maintain physical activity and begin to gradually reload the tendon while avoiding highly provocative loads. It is often possible to keep running by temporarily reducing speed, accelerations, sprinting, hills, stride length and total volume — slow, controlled running can be much better tolerated than a speed session.
You can start with isometric contractions, for example a double-leg isometric bridge (lying on your back, knees bent, feet on the floor, pelvis raised and held for 20 to 45 seconds, 3 to 5 repetitions), adapting the position so that it remains tolerable.
Phase 2 — Progressive strengthening
Once the pain is better controlled, the load is increased gradually: glute bridge (3 × 10-15), single-leg bridge (3 × 8-12), leg curl (3 × 8-12), hip extension (3 × 8-12), hip thrust (3 × 8-12). The aim is to gradually make the muscle capable of producing high forces.
Phase 3 — Work at long musculotendinous lengths
An essential feature of rehabilitation is not to stick only to easy exercises performed with the hip only slightly flexed. Exercises are gradually introduced in which the hip is more flexed, the knee more extended and the load increased: Romanian deadlift, good morning, loaded hip hinge, leg curl with gradually increasing range of motion. The Romanian deadlift (3 to 4 sets of 6 to 10 repetitions, with gradually increasing load, the movement coming from a hip hinge rather than lumbar flexion) is particularly useful for developing the tendon's capacity to withstand load in a lengthened position. The glutes, hip abductors, trunk muscles and pelvic stabilisers must also be developed: lumbopelvic stability allows better control of fast movements and changes of direction.
Phase 4 — Unilateral strengthening
Sport rarely imposes perfectly symmetrical stresses. Single-leg variants are therefore introduced gradually: single-leg Romanian deadlift, single-leg hip thrust, single-leg leg curl, single-leg hip extension, pelvic stability exercises. This stage also makes it possible to look for any functional asymmetry.
Phase 5 — Gradual reintroduction of running
The return begins with brisk walking, slow jogging, then alternating walking and running before continuous running. Duration, volume and speed are then increased gradually, ideally increasing only one parameter at a time. Before returning to normal running, you should ideally have: minimal or no daily pain, good tolerance of walking and strengthening exercises, satisfactory strength, no delayed worsening after sessions and good control of single-leg exercises.
Phase 6 — Reintroducing speed and sprinting
Speed represents a very significant specific load: progression can follow these stages — running at 60-70% of maximum speed, then 70-80%, progressive accelerations, 80-90%, sprinting close to maximum speed, then repeated sprints and changes of direction. For team sports, jumps, bounds, landings, accelerations, decelerations and changes of direction must then be integrated, moving gradually from analytical work to sport-specific work. Before resuming sprints, heavy exercises must be well tolerated, running must be pain-free or almost pain-free, exercises at long muscle lengths must be mastered and sport-specific movements must be reproducible.
Complementary treatments
Massage and manual therapy
May provide temporary symptomatic relief (reduced feeling of muscle tension, improved comfort, easier return to exercise), but does not replace progressive strengthening: a tendon does not regain its mechanical capacity through massage alone.
Extracorporeal shockwave therapy
May be offered in some chronic forms. Favourable results have been found in some studies, but the overall quality of the evidence remains insufficient to make them a standard treatment. To be considered as a possible complement to active rehabilitation.
Corticosteroid injections
Not a first-line treatment. They can sometimes reduce pain temporarily, but their long-term benefit is uncertain; particular caution is needed around a tendon that is already weakened.
PRP (platelet-rich plasma)
Mixed results in the literature. The available data do not allow it to be considered superior to properly conducted rehabilitation; it may possibly be discussed on a case-by-case basis in some resistant chronic forms.
Systematic stretching
Not forbidden, but not the main treatment. During painful phases, stretches combining hip flexion and knee extension can be irritating; mobility must nevertheless remain sufficient for sport.
Surgery
Surgery is rarely necessary for simple proximal tendinopathy; it is not a first-line indication. It may be discussed in specific situations: very disabling chronic pain despite well-conducted rehabilitation, a significant tendon injury or partial tear, proximal avulsion, tendon detachment or major functional deficit.
Proximal hamstring avulsion must be distinguished from chronic tendinopathy: it generally occurs suddenly, with a snap, sudden pain, a tearing sensation, extensive bruising, marked weakness and difficulty walking or running. An MRI is generally needed to determine the number of tendons involved, the degree of retraction and whether the avulsion is complete or partial; management depends on this.
After proximal repair, rehabilitation is much more gradual: protection of the repair, recovery of mobility, muscle reactivation, progressive strengthening, closed-chain work, then running, accelerations, sprinting and sport-specific movements. Follow-up studies show return-to-sport rates often above 90%, but with average timescales of several months.
Recovery time
Healing time varies greatly. A recent, mildly irritable form may improve within a few weeks, whereas chronic tendinopathy may require several months of rehabilitation. The decisive factor is not only the time elapsed since the onset of symptoms, but above all the initial severity, the duration of the condition, the sporting load, the quality and consistency of the rehabilitation programme, the ability to control load and the possible presence of a structural injury. Long-standing pain does not therefore mean a permanently damaged tendon.
Prevention
Prevention relies mainly on maintaining sufficient hamstring capacity: regular hamstring strengthening, glute and trunk work, single-leg exercises, exercises at long muscle lengths and gradual exposure to speed.
In athletes who sprint, it is particularly important to maintain regular exposure to fast running rather than sprinting only after long periods without speed work. Prevention also involves good management of training loads, avoiding increasing volume and intensity at the same time.
Frequently asked questions
Can you run with hamstring tendinopathy?
Should you stop sport completely?
Is stretching bad?
Is strengthening really necessary?
Can I cycle?
Is strength training allowed?
Is shockwave therapy effective?
Is PRP recommended?
When should you have an MRI?
Can you have tendinopathy without doing sport?
Common mistakes
Stopping moving altogether: complete rest leads to a reduction in tendon capacity.
Going straight back to sprinting: the disappearance of pain does not mean the tendon is ready to withstand maximum speed.
Doing only stretching, which does not sufficiently restore the tendon's mechanical capacity.
Relying only on massage: it provides relief but is not the main stimulus for recovery.
Strengthening only in shortened positions, without working on tolerance at long musculotendinous lengths.
Neglecting the lumbopelvic chain, even though the hamstrings work together with the entire lower limb and the pelvis.
Returning to sport as soon as the pain disappears, without a specific progression.
Increasing volume and intensity at the same time — a common way of reactivating symptoms.
Key points — Institut Basque du Coureur
Proximal hamstring tendinopathy most often reflects a progressive intolerance of the tendon to load, not simple inflammation. The typical picture is deep pain in the lower buttock, triggered by running, accelerations, sprinting, exercises at long muscle lengths or prolonged sitting. Diagnosis is mainly clinical; imaging is useful when there is doubt, when a significant injury is suspected or when progress is atypical. Treatment relies above all on education, load management, progressive strengthening, running retraining and the gradual reintroduction of speed. The main goal is not simply to make the pain disappear: a healed hamstring is one that is once again able to withstand the demands of the sport practised.
- Goom TSH, Malliaras P, Reiman MP, Purdam CR. Proximal Hamstring Tendinopathy: Clinical Aspects of Assessment and Management. J Orthop Sports Phys Ther. 2016;46(6):483-493.
- Cacchio A, Borra F, Severini G, et al. Rehabilitation of proximal hamstring tendinopathy: a systematic review.
- Dizon P, Jeanfavre M, Leff G, Norton R. Comparison of Conservative Interventions for Proximal Hamstring Tendinopathy: A Systematic Review and Recommendations for Rehabilitation. Sports (Basel). 2023;11(3):53.
- Paton BM, Read P, van Dyk N, et al. London International Consensus and Delphi study on hamstring injuries part 1: classification. Br J Sports Med. 2023;57(5):254-265.
- Paton BM, Read P, van Dyk N, et al. London International Consensus and Delphi study on hamstring injuries part 3: rehabilitation, running and return to sport. Br J Sports Med. 2023;57(5):278-291.
- van der Made AD, Almusa E, White NJ, et al. Proximal Hamstring Tendon Injuries: Diagnosis and Management.
- Cuthbert M, Ripley N, McMahon K, et al. Evidence-Based Management and Factors Associated With Return to Play After Acute Hamstring Injury in Athletes: A Systematic Review.
- Lempainen L, Sarimo J, Mattila K, et al. Proximal hamstring tendinopathy: results of surgical management and factors associated with outcome.
- Bodendorfer BM, Curley AJ, Kotler JA, et al. Return to Sport After Proximal Hamstring Tendon Repair: A Systematic Review.