
Definition
Compartment syndrome is an abnormal increase in pressure inside a muscle compartment, an anatomical space bounded by structures with little capacity to stretch — mainly fasciae. The lower leg contains several muscle compartments: the anterior compartment, the lateral compartment, the superficial posterior compartment and the deep posterior compartment.
Two situations must be clearly distinguished, as they differ in mechanism, urgency and management.
Acute compartment syndrome
It occurs suddenly, usually after trauma or a fracture, a crush injury, a haemorrhage, vascular reperfusion or, more rarely, exceptional or prolonged exertion. It is a medical and surgical emergency, because the rapid rise in pressure can compromise muscle and nerve perfusion in the limb.
Chronic exertional compartment syndrome
It develops gradually during exercise: pressure rises in one or more compartments during exertion, causing pain, a feeling of tightness or swelling, sometimes with neurological symptoms. The clinical picture is very characteristic: pain comes on during exercise after a fairly reproducible duration or distance, then gradually disappears after stopping. This is the form that mainly affects runners, endurance athletes and some military personnel — and it is the one covered in the rest of this guide.
Anatomy
A muscle compartment is a relatively closed space. It contains muscles, blood vessels, nerves and connective tissue, all enclosed by a fascia with relatively little capacity to stretch. During exercise, muscle blood flow increases and muscle volume also increases; normally, the compartment adapts to this increase in volume. In chronic exertional compartment syndrome, this adaptation becomes insufficient and intracompartmental pressure then gradually rises.
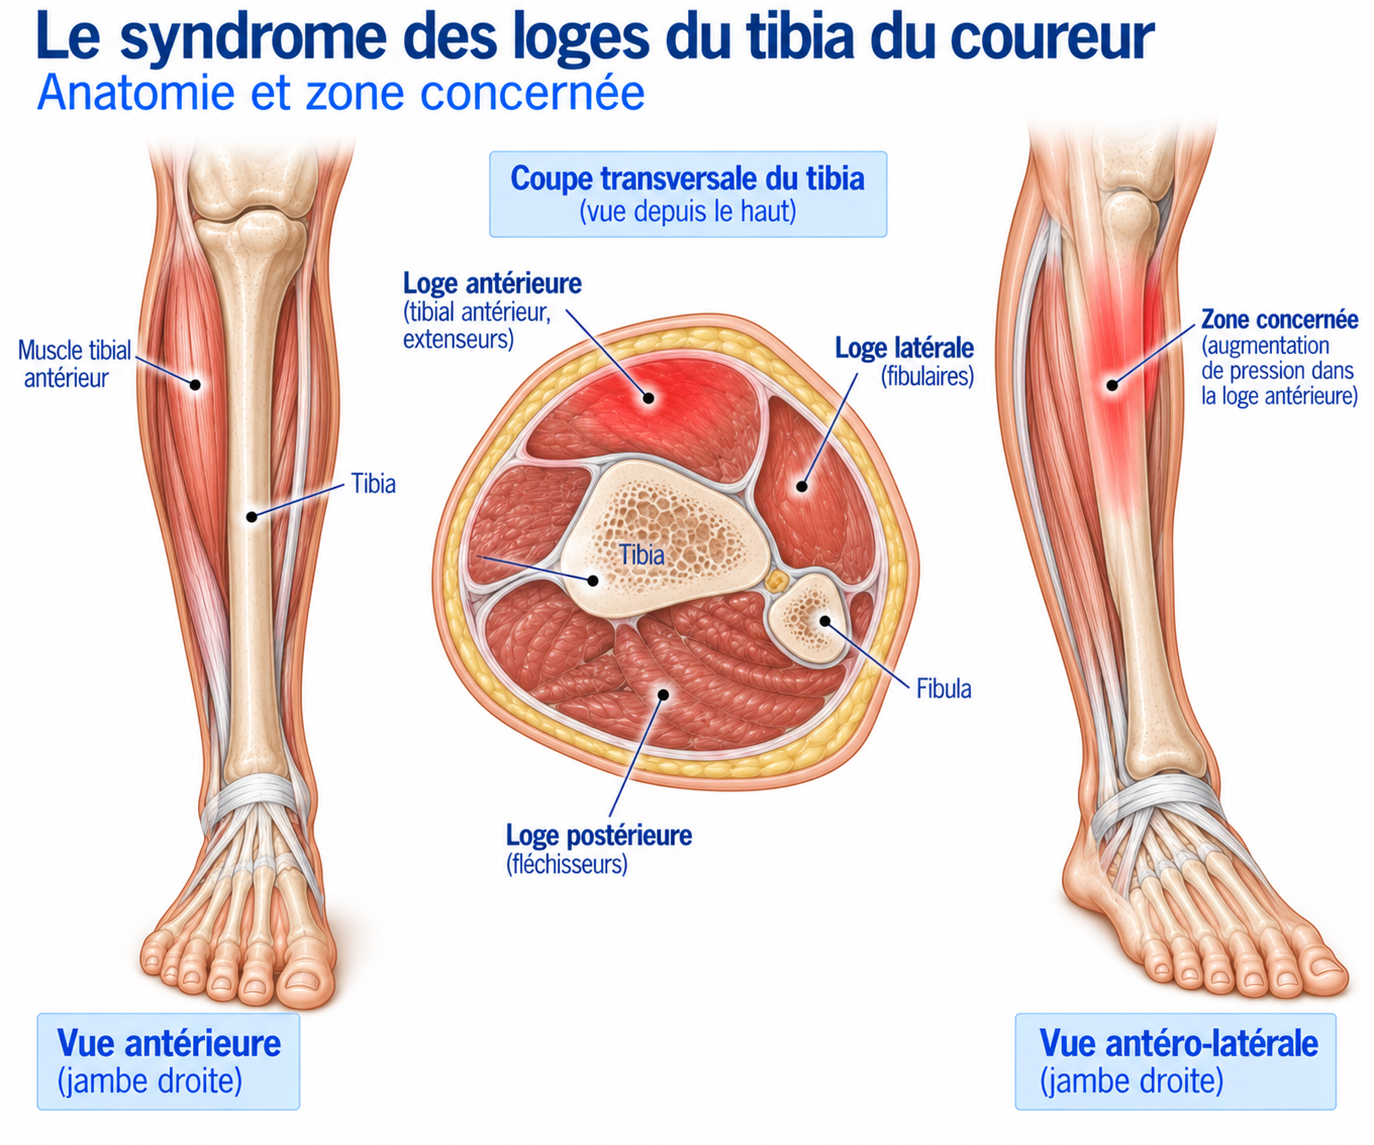
🔍 Click on the image to enlarge it
The four compartments of the lower leg
Anterior compartment — this is the classic location. It contains the tibialis anterior, the extensor digitorum longus, the extensor hallucis longus and the deep fibular nerve. Involvement can cause anterolateral leg pain, marked tightness, sometimes paraesthesia on the top of the foot and weakness of dorsiflexion or toe extension.
Lateral compartment — it mainly contains the fibularis longus, the fibularis brevis and the superficial fibular nerve. Symptoms may include lateral leg pain, a feeling of pressure and paraesthesia on the top of the foot.
Superficial posterior compartment — it contains the gastrocnemius, the soleus and the plantaris. Pain tends to be posterior and can be confused with a triceps surae condition.
Deep posterior compartment — it contains the tibialis posterior, the flexor digitorum longus, the flexor hallucis longus and the tibial nerve. This compartment is harder to diagnose and must be distinguished in particular from shin splints, a stress fracture or tibialis posterior tendinopathy.
Pathophysiology
The exact mechanism is still not fully understood. Put simply, during exercise: increased blood flow leads to increased muscle volume, which leads to increased pressure in the compartment, which leads to a reduced perfusion gradient, resulting in pain and, possibly, neurological symptoms. Several factors may contribute: muscle hypertrophy, low fascial compliance, a marked increase in blood flow, changes in running mechanics, high training volume, sudden changes in terrain or intensity. However, compartment syndrome should not be reduced simply to the idea of a “muscle that is too big”: the relationship between measured pressure, symptoms and the true pathophysiology is still debated. The phenomenon is therefore more a problem of mechanical tolerance and pressure in a closed space than a simple muscle inflammation.
Epidemiology
Chronic exertional compartment syndrome mainly affects physically active people. It is particularly well described in runners, trail runners, endurance athletes, military personnel and athletes who perform repetitive activities placing heavy demands on the lower limbs. The anterior compartment is the most typical location.
It is a well-described cause of exercise-related leg pain in runners, but it remains less common than some other causes such as tibial stress syndromes or muscle injuries. Diagnosis should therefore remain cautious, as exercise-related leg pain has many other causes.
Causes & risk factors
No single factor can predict with certainty the onset of chronic exertional compartment syndrome. Nevertheless, the following factors are frequently found; they are not necessarily direct causes but can alter the load applied to the different compartments.
Training-related factors
Sudden increase in mileage, increased intensity, returning too quickly after a break, more hill sessions, abrupt change of terrain, increased interval training volume.
Biomechanical factors
Recent change in running technique, marked increase in cadence or stride length, change of shoe type, change of drop, major change in running surface.
Symptoms
The classic presentation is extremely reproducible. Athletes often describe it like this: “After 15 minutes, my leg becomes hard and painful. If I stop, it goes away.” Symptoms may include pain, a feeling of tightness, a feeling of swelling, cramp, burning, numbness, pins and needles or muscle weakness.
Reproducibility is particularly important: pain often comes on after a similar duration, a similar distance or at a similar intensity — for example, it consistently appears after 20 minutes of running and then disappears 10 to 20 minutes after stopping. This reproducibility is highly suggestive.
If exercise is continued despite the pain, the pain increases, the feeling of pressure becomes stronger, paraesthesia may develop, muscle weakness may occur and performance declines. In advanced forms, the athlete may be forced to stop completely.
Clinical examination
The clinical examination should ideally be carried out at rest, then immediately after the exercise that usually triggers the symptoms — this is a key point.
At rest, the examination may be completely normal. In particular, the clinician looks for provoked pain, a neurological deficit, muscle asymmetry, a muscle hernia, vascular abnormalities, a tendon abnormality or bone pain.
After exercise, the clinician looks for increased compartment tension, tenderness on palpation, pain on muscle stretching, motor deficit and sensory disturbances. A normal examination at rest in no way rules out chronic exertional compartment syndrome.
Functional tests
The aim is to reproduce the symptoms, for example by running on a treadmill or outdoors, climbing stairs, jumping or doing exercises specific to the athlete’s sport. The test should ideally reproduce the athlete’s usual speed, duration, gradient and symptoms. A negative test performed at low intensity does not necessarily rule out the diagnosis.
Further tests
X-rays
Useful for looking for a bone injury, a fracture or a structural abnormality, but imaging alone is generally not sufficient to diagnose compartment syndrome.
MRI
Looks for a stress fracture, a bone stress reaction, a muscle injury, a tendinopathy or a vascular condition. However, an MRI performed at rest may be normal in exertional compartment syndrome; post-exercise MRI protocols have been studied but do not currently replace a specialist clinical assessment.
Intracompartmental pressure measurement
Long considered the reference test, it involves measuring the pressure in the compartment before exercise and then after exercise that reproduces the symptoms. The Pedowitz criteria, in particular, proposed the following thresholds: resting pressure ≥ 15 mmHg, pressure immediately after exercise ≥ 30 mmHg, pressure at 5 minutes ≥ 20 mmHg. However, these thresholds should not be regarded as absolute, universal values: recent data highlight the heterogeneity of protocols, the variability of measurements and the lack of complete validation, which means the measured pressure must always be interpreted in light of the clinical picture.
Clinical exercise test
Compartment syndrome is a dynamic condition: an optimal assessment seeks to identify the triggering exercise precisely, reproduce it, document the symptoms and then examine the patient immediately afterwards. An examination performed only at rest is a common pitfall.
Differential diagnoses
Shin splints / medial tibial stress syndrome
More diffuse pain along the medial border of the tibia which, unlike compartment syndrome, may persist after exercise stops.
Stress fracture
Pain is often more localised, may come on with less and less exertion and may then become present at rest.
Bone stress reaction
Same reasoning as for stress fracture, but with a less advanced injury.
Tendinopathy
Depending on location: Achilles, tibialis posterior, fibular or tibialis anterior.
Soleus syndrome
Can reproduce exercise-related posterior leg pain.
Nerve involvement
In particular of the fibular nerve or tibial nerve, or lumbar radiculopathy.
Vascular condition
To look for in particular: arterial claudication, popliteal artery entrapment syndrome, arterial endofibrosis in athletes, other vascular abnormalities.
Muscle stress syndrome
A muscle injury or triceps surae overload can also reproduce exercise-related symptoms.
Treatment
Conservative management: general principles
Non-surgical treatment may be tried, particularly when symptoms are moderate, when the diagnosis remains uncertain, in some runners who are able to modify how they train, or when the athlete accepts a reduction in activity level. Strategies may include modifying training, temporarily reducing intensity, adapting running technique, mobility and strengthening work, rehabilitation, changing terrain, adapting footwear and, where appropriate, insoles depending on the biomechanical profile. However, the results of conservative treatment remain highly variable.
Rehabilitation — Phase 1: reduce the triggering load
The aim is not necessarily to stop all activity, but to identify the trigger threshold. For example, if symptoms appear after 20 minutes, running for 10 to 15 minutes may be possible; splitting sessions may be useful; temporarily replacing some sessions with cycling, swimming or the elliptical trainer can help maintain fitness. The aim is to maintain cardiovascular fitness without repeatedly reproducing the syndrome.
Rehabilitation — Phase 2: optimise biomechanics
Depending on the athlete's profile, work may focus on cadence, stride length, pelvic position, lower limb control, ankle mobility, triceps surae strength, intrinsic foot muscle strength and neuromuscular control. There is no universal running technique that can "cure" compartment syndrome: changes to running gait must be individualised and aim to reduce the stresses identified in the athlete, without creating new stresses elsewhere.
Rehabilitation — Phase 3: muscle strengthening
Strengthening may include, for the triceps surae: heel raises, single-leg work, loaded work, eccentric or heavy slow resistance work depending on the goals; for the hip muscles: gluteus medius, gluteus maximus, abductors; for the foot: intrinsic muscles, arch control, balance exercises; and for the neuromuscular chain: single-leg squat, step-down, lunges, proprioceptive work. The aim is to make the lower limb more efficient and more tolerant to load.
Rehabilitation — Phase 4: gradual return to running
A possible progression: walking, then alternating walking and running, then continuous running, then increasing duration, then intensity, then hills, then intervals, then return to sport-specific activity. The key criterion remains the onset of symptoms: avoid systematically trying to "push back" the pain threshold at every session.
Surgery
When should surgery be considered?
Surgery is generally discussed when the diagnosis is sufficiently robust, the symptoms are typical and disabling, the athlete wishes to continue their sport, conservative treatment has failed or is insufficient, and when compartment involvement has been objectively confirmed where indicated.
Fasciotomy: the reference treatment
Surgical treatment consists of performing a fasciotomy, that is, opening the fascia of the compartment to reduce the stress caused by the increased pressure. Surgery can be open, minimally invasive or endoscopic, depending on the surgical team and the compartments involved. Recent literature confirms that fasciotomy remains the reference surgical treatment for chronic exertional compartment syndrome that does not respond to conservative treatment.
Results of surgery
Results are generally favourable in well-selected patients, but studies report very variable rates of satisfaction and return to sport: in a recent systematic review, satisfaction after fasciotomy was reported at roughly 42 to 94%, and return to sport at 26 to 100%. This wide variability reflects, among other things, the different compartments involved, surgical techniques, study populations, the success criteria used, whether the athletes were civilian or military, and recurrences or residual symptoms. Surgery is therefore no absolute guarantee of a return to the previous level.
Why does surgery sometimes fail?
Several mechanisms are possible: incorrect initial diagnosis, wrong compartment identified, incomplete decompression, unrecognised involvement of several compartments, recurrence, adhesions, associated nerve involvement, or another coexisting cause of pain. It is therefore particularly important to reassess the diagnosis before considering revision surgery.
Two or four compartments?
How many compartments to release depends on the clinical picture and the pressures measured. Some studies show comparable results between two-compartment and four-compartment fasciotomy, but the data remain of limited quality and heterogeneous: the decision should therefore be individualised rather than based on a fixed rule.
Recovery time
Rehabilitation after surgery
Recovery after fasciotomy is gradual, in four phases. Phase 1 — protection: wound healing, reduction of oedema, recovery of range of motion, gradual return to walking. Phase 2 — muscle recovery: progressive mobility, strengthening, balance and neuromuscular control work. Phase 3 — return to impact: gradual introduction of brisk walking, small hops, single-leg hops and then light running. Phase 4 — return to running: progression from slow running to duration, volume, intensity, intervals and then sport-specific terrain. However, postoperative protocols remain heterogeneous in the literature and no universal timeline can be considered validated.
Criteria for returning to running
The return should not be based solely on time since surgery. The criteria sought are, clinically: a healed scar, no significant oedema, minimal or no pain, no paraesthesia; in terms of mobility: satisfactory ankle mobility and range of motion close to the opposite side; in terms of strength: satisfactory recovery of the triceps surae, good strength in the lower limb muscles and no significant functional deficit; and functionally: the ability to perform brisk walking, stair climbing, jumps and single-leg or sport-specific exercises without significant pain.
Return to sport
The return to sport should be gradual, increasing only one variable at a time: slow running on flat ground, then gradually increasing running time, then weekly volume, then introducing changes of pace, then hill work, then intervals, then returning to the specific demands of the sport. Avoid resuming volume, speed, elevation gain and specific sessions all at the same time.
Prevention
No single factor can predict with certainty the onset of compartment syndrome, but careful management of the identified contributing factors remains the best preventive approach: avoid sudden increases in mileage or intensity, favour a gradual return after a break, and limit the number of hill sessions and overly rapid increases in interval training volume.
From a biomechanical point of view, any major change in running technique, cadence, stride length, shoe type, drop or running surface should be introduced gradually rather than abruptly, so as not to change the load applied to the different muscle compartments too quickly.
Frequently asked questions
Is compartment syndrome dangerous?
Can I run with chronic compartment syndrome?
Is pain that disappears when you stop typical?
Is an MRI enough to make the diagnosis?
Is it always necessary to measure intracompartmental pressures?
Does surgery provide a permanent cure?
Can more than one compartment be affected?
Is it common in runners?
Common mistakes
Confusing compartment syndrome with shin splints: both can cause leg pain in runners, but they are managed differently.
Relying on an examination at rest alone, when the syndrome is dynamic.
Relying solely on a pressure value, without interpreting it in light of the clinical picture.
Obtaining a normal MRI at rest and concluding that the diagnosis is ruled out.
Systematically continuing to run up to the pain threshold, even though this does not necessarily improve the situation.
Operating without having ruled out differential diagnoses: a fasciotomy does not treat a stress fracture, a vascular condition or a radiculopathy.
Resuming intense sessions immediately after surgery, when muscle and fascial recovery requires a progression.
Key points — Institut Basque du Coureur
Chronic exertional compartment syndrome should be considered in the presence of exercise-induced leg pain that is highly reproducible, accompanied by a feeling of tightness or pressure, sometimes associated with paraesthesia or weakness, and that subsides after stopping. Diagnosis relies above all on a very precise clinical history and reproduction of the symptoms, supplemented where necessary by tests to rule out other causes and, in appropriate situations, by intracompartmental pressure measurement. Treatment depends on the athlete's sporting goals and the severity of the symptoms: conservative management may be tried, with training adjustments, rehabilitation and biomechanical work; when symptoms remain disabling despite this management and the diagnosis is sufficiently established, fasciotomy is the reference surgical treatment. Finally, this chronic form must always be distinguished from acute compartment syndrome, which is a surgical emergency.
- Roberts AJ, Franklyn-Miller A. The chronic exertional compartment syndrome: diagnosis, management, and outcomes. Sports Med. 2012.
- Brennan FH, Kane SF. Diagnosis, treatment options, and rehabilitation of chronic lower leg exertional compartment syndrome. Curr Sports Med Rep. 2003.
- Pedowitz RA, Hargens AR, Mubarak SJ, et al. Modified criteria for the objective diagnosis of chronic compartment syndrome of the leg. Am J Sports Med. 1990.
- Aweid O, Del Buono A, Malliaras P, et al. Systematic review and recommendations for diagnosis and treatment of chronic exertional compartment syndrome. Br J Sports Med.
- de Bruijn JA, van Zantvoort APM, Schouten HJ, et al. Clinical Consensus on Diagnosis and Treatment of Patients with Chronic Exertional Compartment Syndrome of the Leg: A Delphi Analysis. Sports Med. 2022.
- Dean RS, Farley KX, Waterman BR, et al. Chronic exertional compartment syndrome is frequently diagnosed through static compartment pressure measurements and managed with fasciotomy: a systematic review. J ISAKOS. 2024.
- Roberts AJ, Krishnasamy P, Quayle JM, et al. Chronic exertional compartment syndrome of the lower extremity: diagnosis and surgical treatment. JBJS Essential Surgical Techniques.
- Gawel RJ, Kemler BR, Coladonato C, Freedman KB. Rehabilitation and return to activity criteria after operative management of chronic exertional compartment syndrome of the leg: a systematic review. Clin J Sport Med. 2024.
- van den Brand JGH, Nelson T, Verleisdonk EJMM, van der Werken C. The diagnostic value of intracompartmental pressure measurement in chronic exertional compartment syndrome.
- Tucker AK. Chronic exertional compartment syndrome of the leg. Curr Rev Musculoskelet Med. 2010.
Similar injuries
Popliteal artery entrapment syndrome
A rare but serious vascular compression of the popliteal artery that causes exercise-induced pain.
Tibial stress fracture
A tibial micro-fracture caused by repeated stress, requiring a mandatory break from running to allow the bone to heal.
Tennis leg
Acute muscle tear of the calf (medial gastrocnemius), occurring suddenly during exertion in runners.